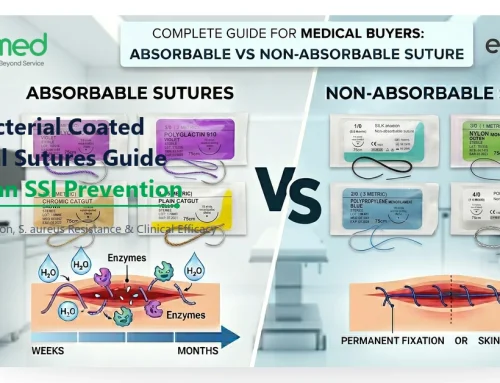
In emergency trauma wound management, pediatric laceration repair, and elective plastic surgery, closing surgical incisions efficiently while minimizing operative time and scarring is a paramount objective. While conventional sterile surgical sutures remain the bedrock of tissue approximation across deep layers, topical cyanoacrylate tissue adhesives (skin glues) have surged as a high-speed alternative for epidermal closure. This comparative surgical engineering analysis evaluates 2-octyl cyanoacrylate against monofilament sutures, focusing on tensile holding force, microbial barrier performance, cosmetic scoring, and healthcare system ROI.

1. Polymerization Dynamics of Medical Cyanoacrylates
Modern medical skin glues primarily utilize 2-Octyl Cyanoacrylate (2-OCA) 그리고 N-Butyl Cyanoacrylate (n-BCA). Upon exposure to ambient air moisture and surface tissue fluids, cyanoacrylate monomers undergo exothermic anionic polymerization within 30 to 60 seconds, creating a pliable three-dimensional polymer bridge that bonds the opposing stratum corneum layers.
Crucially, 2-OCA formulations provide four times the flexural strength and significantly higher elasticity than early short-chain methyl cyanoacrylates, allowing the adhesive film to move naturally with patient skin without premature cracking or flaking.
2. Clinical & Mechanical Comparison: Glue vs Sutures
| Clinical Parameter | 2-Octyl Cyanoacrylate Skin Adhesive | Monofilament Sutures (e.g., Nylon / Polypropylene) | Subcuticular Absorbable (PGA / Monocryl) |
|---|---|---|---|
| Application Speed | Ultra-fast (1–2 minutes total closure time) | Moderate (5–12 minutes depending on throws) | Detailed (8–15 minutes continuous stitch) |
| Tensile Holding Capacity | Equivalent to 5-0 monofilament in low-tension areas | High tensile burst strength across all planes | High holding force with gradual absorption |
| Local Anesthetic Need | Zero local anesthesia required in most trauma cases | Mandatory subcutaneous lidocaine infiltration | Mandatory local anesthesia |
| Microbial Barrier Function | Hermetic barrier preventing Gram+ and Gram- ingress | Puncture tracts can act as bacterial conduits | Completely buried beneath epidermis |
| Secondary Removal Visit | None: sloughs off naturally in 7–10 days | Mandatory clinic visit at 5–10 days for suture removal | None: enzymatic/hydrolytic bioabsorption |
| High-Tension / Joint Suitability | Poor (contraindicated on knees, elbows, scalp) | Excellent (accommodates high flexion and stress) | Requires deep fascial anchor sutures |
3. Indications and Absolute Contraindications
Approved Indications:
- Clean, low-tension linear surgical incisions (laparoscopy port sites, hernia repairs, cesarean skin closures).
- Pediatric facial and forehead lacerations where needle phobia and anxiety are prominent.
- Supplementary seal over buried subcuticular absorbable suture lines.
Absolute Contraindications for Skin Glue:
- Mucosal & Wet Surfaces: Oral cavity, vermilion border, perineum, or heavily exuding contaminated wounds.
- High Dynamic Tension: Joint creases, hands, feet, or wounds with active skin tension unless supported by deep dermal tension-relieving sutures.
- Bite Wounds & Animal Scratches: High bacterial colonization risks require open drainage or interrupted suturing to prevent trapped abscesses.
⚠️ Clinical Safety Rule: Deep Tension Relieving Sutures
Topical skin adhesive is exclusively an epidermal closure device. It must never be placed inside the wound bed, as unpolymerized cyanoacrylate causes foreign-body granulomatous inflammation. Deep tissue approximation must always be achieved beforehand using braided PGA or monofilament absorbable sutures.
4. Frequently Asked Questions (FAQ)
Can patients shower immediately after skin adhesive application?
Yes. Fully polymerized 2-octyl cyanoacrylate forms a water-resistant microbial barrier. Patients can shower lightly, provided they avoid soaking, scrubbing, or applying topical antibiotic ointments that dissolve the cyanoacrylate film.
What is the cosmetic difference at 3 months post-op?
Clinical trials indicate equivalent cosmetic outcomes between topical 2-OCA and fine 5-0/6-0 monofilament sutures, with adhesives showing slightly reduced "railroad track" cross-hatching marks because no needle punctures cross the epidermis.
Comprehensive Surgical Wound Closure Supply
Shevenmed manufactures international standard surgical sutures, absorbable sutures, and aseptic surgical consumables for hospital networks and distributors worldwide.